

Diagnosis
Normalising and correctly communicating a diagnosis can be therapeutic in itself. Communicating FND a diagnosis should be similar to communicating any other neuro(psychological) condition:
give the name of the diagnosis
explain on what basis you diagnosed the patient with this disorder
give some brief information about the disorder and its mechanisms
tell you that the disorder is treatable and that multidisciplinary treatment is optimal





Important cues to consider when communicating your diagnosis:
What terminology to use?
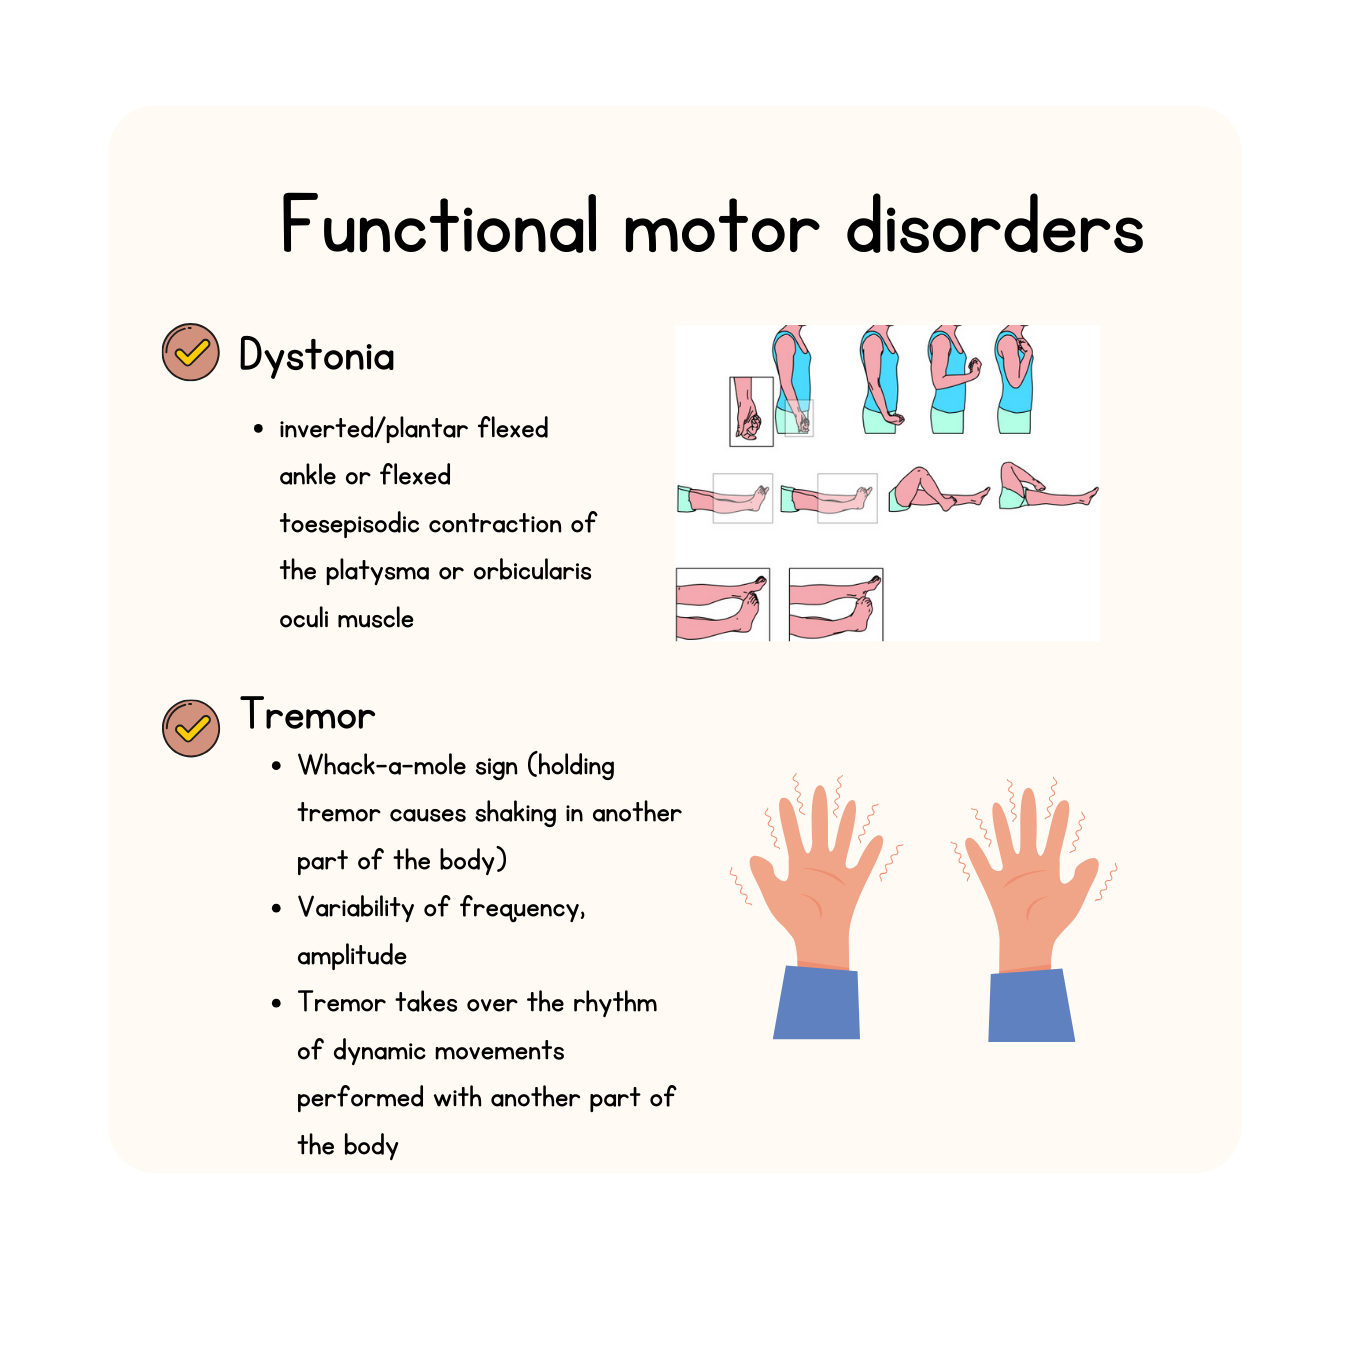
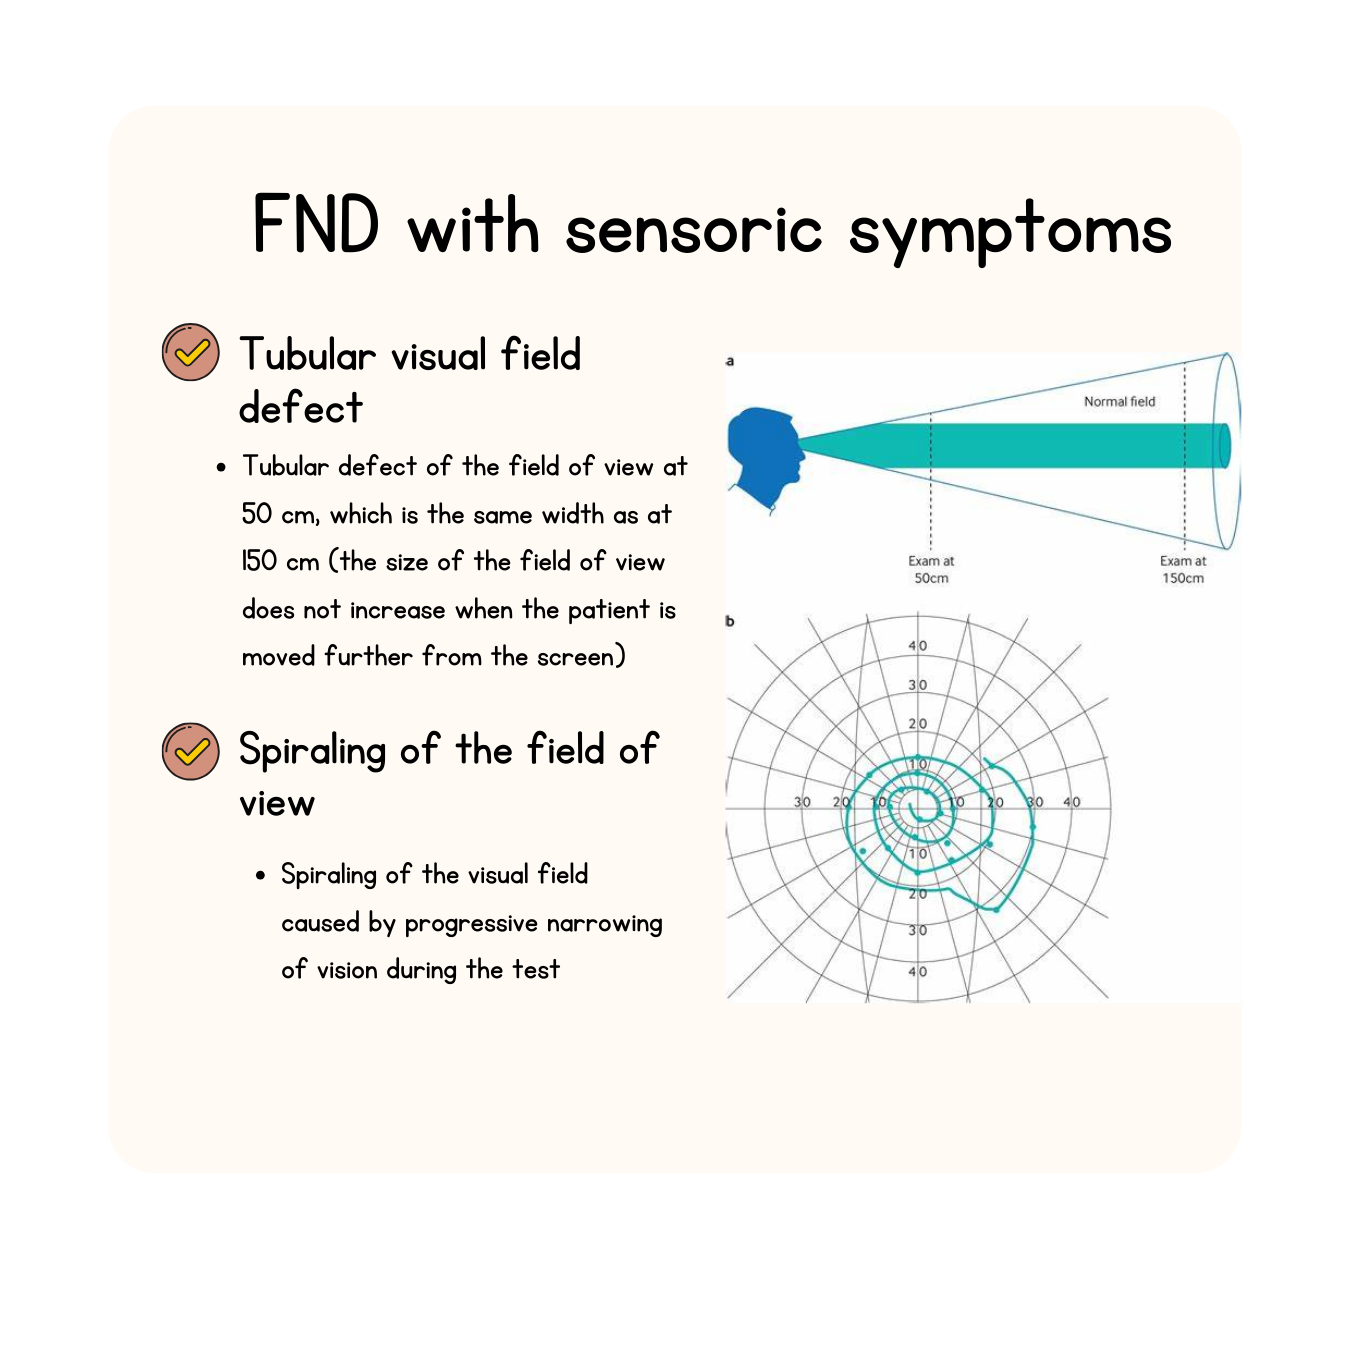
Regarding terminology, it is most highly recommended that you use the term “functional neurological disorder,” as it is etiologically neutral and, at the same time, the most accurate, since it does not imply that the cause is exclusively psychogenic. Show the patient the positive diagnostic signs (described above), as this will help them see that the diagnosis was not made by ruling out other neurological conditions, and at the same time, you will demonstrate that their condition is potentially reversible (e.g., through distraction techniques).
Using analogies. Yes or no?
Analogies such as PC model or software and hardware analogies. Explain to the patient that their hardware is intact, while the software is faulty. If patients are experiencing several different symptoms, you can explain to them that there has been a "software crash" and that one of the goals of treatment is to make an "update in their software system". While the analogy between software and hardware is useful and allows for a better understanding, it is also incomplete as it does not cover all the factors that contribute to the maintenance of the disorder, so it is recommended to complement the explanation with a PC model.
I believe you!
It is crucial to use language that does not reflect prejudice, is compassionate, and makes the person feel heard and accepted. Emphasize that the symptoms they are experiencing are real and that they are not imagining them, as this significantly helps establish a trusting therapeutic relationship. Most people with FND have had negative past experiences with healthcare providers, who told them that “it’sall in their head”and that they are actually faking their symptoms. In the early stages of diagnosis, it is important to explain to the patient that they play a significant role in their own recovery process (Finkelstein et al., 2022).
Educating and correctly explaining the psychological mechanisms of the disorder
Accepting and learning about the diagnosis itself is one of the most important keys to potential recovery, which is why communicating the diagnosis correctly is truly important! Due to the historical stigma surrounding FND, it is helpful to take the time to explain the psychological background of the disorder. It is crucial not to confuse a risk factor (e.g., psychological trauma or a stressful life event) with the cause, and to clarify that there are no separate neurological and psychological patterns in the brain—rather, the mind and body are inextricably linked. Psychological factors play an important role, but some people with FND may not recognize the need for psychological treatment; therefore, it is important not to pressure or persuade them, but rather to reassure them that they will have the opportunity to clarify any concerns regarding the diagnosis at their next follow-up appointment.
An incentive to participate
You can also ask the person at FND how certain they are about their diagnosis, and if they aren’t 100% certain, ask them what’s “holding them back.” It’s important to encourage honesty while also expressing unconditional acceptance and empathy, despite any potential disagreements. Refer them to helpful websites with verified information at FND, as this knowledge will empower them and provide additional insight into their symptoms. The opportunity to view or read stories from other patients can help her feel that she is not alone and satisfy her need to belong and be heard (Finkelstein et al., 2022).
A 28-year-old man gradually develops paralysis and numbness in his left leg after a minor but painful ankle injury. Doctors found no organic cause for the paralysis and he felt rejected, suggesting that it was all in his head. He had a difficult childhood but did not meet the criteria for a diagnosis of clinical depression.
-
There is clear positive evidence of a diagnosis of FND with a pattern of weakness and physical signs including Hoover's sign.
-
Explain that it is a functional neurological disorder.
-
Explain that this is a potentially reversible condition and explain that the hardware is not damaged (hardware; brain) while the software is (software; central nervous system)
-
It is very complicated. Research risk factors at the patient's pace, not yours. Think about how you would explain the cause of a stroke in an ex-smoker or a non-smoker. Do not turn a risk factor into a "cause" of the problem.
-
It is important to consider other investigations, as people with FNM often have other medical conditions that may trigger or increase their vulnerability to the disorder.
-
Physiotherapy can help to re-train the brain so that movements become automatic and normal again. Psychological therapy is useful in terms of understanding why the disorder has developed and how symptoms can be relieved.

-
Adams, C., Anderson, J., Madva, E. N., LaFrance Jr, W. C., in Perez, D. L. (2018). You've made the diagnosis of functional neurological disorder: now what?. Practical neurology, 18(4), 323-330.
Aybek, S., and Perez, D. L. (2022). Diagnosis and management of functional neurological disorder. bmj, 376.
Bennett, K., Diamond, C., Hoeritzauer, I., Gardiner, P., McWhirter, L., Carson, A., and Stone, J. (2021). A practical review of functional neurological disorder (FND) for the general physician. Clinical Medicine, 21(1), 28.
Drane, D. L., Fani, N., Hallett, M., Khalsa, S. S., Perez, D. L., and Roberts, N. A. (2021). A framework for understanding the pathophysiology of functional neurological disorder. CNS Spectrums, 26(6), 555-561.
Espay, A. J., Aybek, S., Carson, A., Edwards, M. J., Goldstein, L. H., Hallett, M., ... in Morgante, F. (2018). Current concepts in diagnosis and treatment of functional neurological disorders. JAMA Neurology, 75(9), 1132-1141.
Finkelstein, S. A., Adams, C., Tuttle, M., Saxena, A., and Perez, D. L. (2022). Neuropsychiatric treatment approaches for functional neurological disorder: a how to guide. In Seminars in Neurology (Vol. 42, No. 02, pp. 204-224). Thieme Medical Publishers, Inc..
Finkelstein, S. A., Cortel-LeBlanc, M. A., Cortel-LeBlanc, A., in Stone, J. (2021). Functional neurological disorder in the emergency department. Academic Emergency Medicine, 28(6), 685-696.
Hallett, M., Aybek, S., Dworetzky, B. A., McWhirter, L., Staab, J. P., in Stone, J. (2022). Functional neurological disorder: new subtypes and shared mechanisms. The Lancet Neurology, 21(6), 537-550.
Stone, J., Burton, C., in Carson, A. (2020). Recognising and explaining functional neurological disorder. bmj, 371.
Stone, J., Carson, A., and Hallett, M. (2016) Explanation as treatment for functional neurological disorders. Handbook of clinical neurology, 139, 543-553.